Next part: An Overweight Rescue Dog Needed Daily Walks, but No Adopter Wanted the Work — Then an 89-Year-Old Heart Patient Realized They Had Been Given the Same Prescription
Part 2 — Two Medical Plans and One Teal Leash
My mother had never been inactive before her surgery.
Georgia Sandoval raised four children, worked twenty-eight years in an elementary-school cafeteria, maintained a vegetable garden, and continued driving herself to church well into her eighties. Even after arthritis slowed her, she remained in motion.
Heart surgery changed her confidence before it changed anything else.
She began treating fatigue as danger. A brief increase in breathing convinced her she should sit down. Every outdoor step seemed to ask whether her body could still be trusted.

Her cardiologist, Dr. Samuel Levin, explained that recovery required safe, progressive activity, not permanent rest. Georgia enrolled in cardiac rehabilitation, where staff monitored her heart rate, blood pressure, oxygen level, and response to exertion.
She participated.
At home, she stopped.
The clinical hallway had handrails, nurses, and machines. Her neighborhood had uneven pavement, heat, barking dogs, and the possibility of being seen struggling.
I was fifty-eight and lived twelve minutes away. I offered to walk with her each morning, but my mother disliked being managed by her daughter.
“I know what the doctor said,” she would answer.
Then she remained beside the window.
Rosie entered our lives through my friend Carla, who volunteered with a local rescue. Carla sent me a photograph of a chocolate-colored dog lying beneath an air-conditioning vent, her abdomen spread wide against the tile.
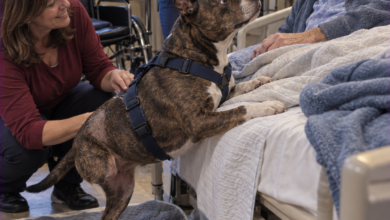
The photograph made Rosie’s condition immediately visible. There was no curve between her ribs and hips. Fat covered her waist, chest, and tail base. When she stood, she shifted slowly and planted her feet wide for stability.
A veterinarian, Dr. Melissa Grant, had already examined her. Rosie’s abdomen was enlarged from excess body fat, not fluid, pregnancy, or an internal mass. Blood tests found no obvious endocrine disease causing the weight gain.
She weighed eighty-four pounds.
Dr. Grant estimated that a healthier long-term weight would be approximately seventy pounds, adjusted according to body condition and muscle loss. The goal was not rapid loss. Dogs losing weight too quickly can lose muscle, worsen weakness, and develop nutritional problems.
Rosie needed measured calories, joint-conscious exercise, and consistent monitoring.
Her rescue history was ordinary rather than sensational. Her previous owner had entered assisted living after a fall, and relatives could not accommodate a large dog. Records showed that Rosie had gradually gained weight as the owner became less mobile.
She had been loved.
She had also become unhealthy.
I suggested Rosie to Georgia because both had been prescribed walking, but I was careful not to present a dog as medical equipment. Rosie needed a committed caretaker, veterinary expenses, training, and a plan for days when my mother could not handle her.
Georgia first refused.
“I can barely take care of myself.”
“That’s why it would be a foster trial,” I said. “And I would handle anything you can’t.”
The rescue required more than my promise. We submitted a written care plan. I would manage appointments and backup walks. Georgia’s fenced yard would cover bathroom needs during difficult days. Rosie would wear a harness with both front and rear handles if her knees required support.
Dr. Levin cleared Georgia for short, supervised outdoor walks, with firm limits. She was to stop for chest pressure, dizziness, unusual breathlessness, palpitations, or weakness. Morning heat dictated distance. Hydration and medication timing mattered.
Dr. Grant gave Rosie equally strict limits. No jogging. No steep inclines. No forced distance. Walks would begin at three to five minutes on level ground, with paw checks and rest afterward.
We were not launching a ten-thousand-step challenge.
We were trying to reach the gate safely.
At the rescue, Rosie approached Georgia slowly. She smelled the rubber feet of her cane, then sat beside her. Georgia rubbed the white patch beneath the dog’s chin.
Rosie leaned once against her leg.
That was not instant healing or destiny. It was a calm first interaction between two individuals who disliked being hurried.
Georgia agreed to the foster trial.
The following morning, Rosie stopped at the porch threshold. Georgia stopped behind her.
The teal leash hung between them.
Neither wanted to move first.
Finally, Georgia tapped her cane against the concrete and said, “Only to the gate, mija.”
Rosie stepped outside.
Their first recovery plan began with permission to turn back.
Part 3 — When Seventy-Two Steps Became a Route
I counted the first walk because I was afraid of missing a warning sign.
Georgia took thirty-six steps to the gate and thirty-six back. Rosie paused four times and panted lightly near the end. My mother’s breathing increased but settled within two minutes after she sat down.
We entered the numbers in separate logs.
Georgia’s page included distance, pulse, symptoms, and recovery time. Rosie’s included duration, gait, panting, paw condition, and willingness to continue.
The logs prevented enthusiasm from replacing judgment.
On day three, Rosie tried to turn home after twenty steps. Georgia followed without coaxing. On day four, my mother felt lightheaded before leaving, so I walked Rosie while Georgia watched from the porch.
That distinction mattered.
The routine served their health; their health did not serve the routine.
Rosie quickly recognized the sound of Georgia’s walking shoes against the tile. At 6:45 each morning, she moved from her bed to the hallway and sat beside the cane.
Her body remained visibly heavy. Rising required rocking her weight forward, and her knees were stiff during the first several steps. Once moving, however, she investigated every mailbox post.
Georgia began laughing at how little distance they covered.
“We have been walking ten minutes,” she told me one morning, “and your dog has traveled three houses.”
“She’s your foster dog.”
“We’ll see.”
By the end of the second week, they reached the neighbor’s mailbox. The route was approximately six hundred steps round trip for Georgia, fewer for Rosie because canine stride could not be compared directly.
We did not convert Rosie’s movement into human step totals. Her veterinary plan relied on minutes, comfort, and body response.
Georgia’s rehabilitation staff increased her walking goal gradually. On supervised days, she used a clinic treadmill at very low speed. At home, Rosie remained her preferred partner.
The first visible change was not weight.
Rosie began standing when the harness appeared instead of remaining on her bed. Georgia started tying her shoes before I arrived.
Anticipation returned before endurance.
At the end of the first month, Georgia could walk twelve continuous minutes with one planned rest. Rosie could complete the same route without excessive panting, although both moved slowly.
Dr. Grant weighed Rosie every two weeks. The first loss was less than one pound. Georgia appeared disappointed.
The veterinarian was not.
Rapid changes often reflect dehydration rather than healthy fat loss. Rosie’s food had been measured to maintain nutrition while creating a modest calorie deficit. Treats came from her daily allowance, not in addition to it.
Georgia’s progress was similar. Her cardiologist cared more about blood-pressure stability, rehabilitation tolerance, and daily function than the number on a bathroom scale.
Still, the numbers gave my mother something concrete to track.
She taped both charts to the refrigerator.
One side read “Georgia.”
The other read “Rosie.”
During the sixth week, they reached the shaded bench near the corner. The temperature was already rising by seven, so we shifted walks earlier and shortened them whenever humidity climbed.
That morning, Rosie stopped thirty yards from the bench.
She sat and lifted her right front paw.
The pad appeared intact, but the space between two toes was red and swollen. I carried a folding support sling, yet lifting a dog of Rosie’s size without knowing the injury could worsen pain.
We called Dr. Grant and arranged transport.
A foxtail-like grass seed had embedded between the toes, causing localized inflammation. It was removed under light sedation, and Rosie received medication and instructions for several days of restricted activity.
The injury was minor.
Its effect on Georgia was not.
Without Rosie, my mother skipped her home walk. She completed cardiac rehabilitation at the clinic but did not step beyond the porch the next morning.
“You can walk with me,” I said.
“It isn’t the same.”
That response worried Dr. Levin. Rosie had motivated Georgia, but motivation had become dependence. If the dog’s illness or eventual death ended Georgia’s activity, the partnership would become medically fragile.
Dr. Grant raised a parallel concern. Rosie could not be pushed to walk because Georgia needed exercise.
Both patients needed independent safety plans inside a shared routine.
For the next five days, Georgia walked the driveway with me while Rosie rested behind the fence. We kept the dog visible but did not let her follow.
Rosie protested on the first morning by standing at the gate. Georgia almost abandoned her own walk.
Instead, she touched the top rail and said, “You rest. I’ll bring the street back to you.”
Then she completed the driveway twice.
Rosie watched.
On the sixth morning, Dr. Grant cleared the dog for a brief return.
Georgia shortened the leash, checked the healed paw, and walked only to the gate.
They had reached that point weeks earlier.
This time, it did not feel like losing progress.
It felt like learning how to begin again without shame.
Part 4 — The Summer They Learned to Stop Early
South Texas summer could not be treated as a test of determination.
By June, morning temperatures rose quickly, and pavement retained heat before many people realized it. Rosie’s thick body insulation and excess weight increased her risk of overheating. Georgia’s cardiac medications affected how her body responded to heat and dehydration.
Their doctors changed the schedule.
Walks began near sunrise. We checked pavement temperature with the back of a hand, carried water, and chose shaded streets. On extreme days, they walked indoors at a community center.
Georgia initially disliked the indoor route.
“It feels like going in circles.”
Rosie disagreed. The polished floor carried food smells, cleaning solution, rubber shoes, and traces of other dogs. She stopped so often that one lap took nearly ten minutes.
Their pace drew attention.
Some walkers passed them repeatedly. Others slowed to ask about Rosie’s teal harness or Georgia’s heart-rehabilitation badge.
Georgia answered plainly.
“She has to lose weight. I have to use my heart.”
By the fourth month, Georgia averaged approximately 4,000 purposeful steps across the day, including household movement and supervised walks. Rosie’s outdoor exercise totaled twenty to twenty-five minutes, divided into two sessions.
They did not share identical goals.
They shared the decision to appear at the door.
Rosie had lost three pounds by then. Her waist remained difficult to see, but the fat pad across her back had softened. She rose more smoothly and recovered faster after walking.
Georgia’s progress appeared in ordinary tasks. She stopped using the kitchen chair while preparing breakfast. She walked from the parking lot to rehabilitation instead of asking to be dropped at the entrance. She began watering two planter boxes again.
Then she became competitive.
At the community center, another walker showed Georgia a step counter. My mother asked me to buy one. Within a week, she began adding laps after Rosie slowed.
The number became a challenge.
One morning, Georgia reached 6,200 steps by noon and tried to walk again despite unusual fatigue. Rosie lay near the door but did not rise when the harness appeared.
Georgia called her twice.
The dog remained on the tile, breathing normally but clearly uninterested.
I reminded my mother of the rule: refusal counted.
She frowned.
“We’re close to seven thousand.”
“Rosie doesn’t know that.”
Georgia removed the harness.
That afternoon, her blood pressure measured lower than usual, and she felt dizzy when standing. Her rehabilitation nurse advised fluids, rest, and evaluation if symptoms continued. The episode resolved, but Dr. Levin addressed it firmly at the next appointment.
A step goal could guide activity. It could not override symptoms.
“Ten thousand is not a magic number,” he told her. “Your body does not owe a device a result.”
Dr. Grant made the same point about Rosie. Weight loss depended on calorie control, appropriate movement, pain management, sleep, and time. More walking was not automatically better for arthritic knees.
We rewrote the refrigerator chart.
Instead of listing only steps and weight, it included comfort, willingness, recovery, and rest.
Green days meant both could complete planned activity comfortably. Yellow days required shorter distance or indoor movement. Red days meant medical symptoms, pain, excessive heat, or refusal—no optional walk.
Georgia resisted the system for a week.
Rosie accepted it immediately.
On a yellow morning, the dog reached the porch, smelled the heavy air, and turned back inside. Georgia followed, annoyed but compliant.
They walked six short indoor circuits between the living room and back hallway. Rosie’s tail moved each time they passed her water bowl. Georgia laughed by the fourth circuit.
Progress became less photogenic and more sustainable.
At month six, Georgia’s cardiology tests showed better exercise tolerance and improved blood-pressure control. Her weight had decreased gradually, though Dr. Levin emphasized strength and function over appearance.
Rosie had lost six pounds. Her knees remained arthritic, but improved body condition reduced the load they carried.
The foster trial had quietly become permanent months earlier. Georgia signed the adoption documents after Rosie’s paw healed.
On the line asking why she wished to adopt, my mother wrote:
“She stops when I should stop, and she gets up when I should get up.”
The sentence described their partnership better than any step count.
Still, Georgia kept one number in mind.
She wanted to reach 10,000 daily steps—not immediately, not every day, and never by forcing Rosie to cover the same human distance.
The goal remained far away.
Then autumn brought cooler mornings, and Rosie began waiting at the door before the alarm sounded.
Part 5 — The Day the Counter Reached Five Digits
By the eighth month, Georgia and Rosie had divided the morning into stages.
The first walk began at 6:30 and ended after twenty minutes. Rosie rested and ate breakfast. Georgia completed household movement, attended cardiac rehabilitation twice a week, and took another short walk later with me or inside the community center.
Rosie’s veterinary exercise remained capped according to her knees. She did not accompany Georgia for every step.
This distinction allowed them to grow together without pretending their bodies were interchangeable.
Rosie now weighed seventy-five pounds. A slight waist had appeared behind her ribs. Her abdomen remained broad, but it no longer hung as heavily when she walked.
Dr. Grant adjusted food portions as weight declined. Maintaining the same calorie deficit indefinitely could become excessive. The goal was steady improvement while preserving muscle.
Georgia had lost approximately sixteen pounds. More importantly, she could walk continuously for nearly thirty minutes at a pace approved by rehabilitation staff. Her balance improved, and she used the cane mainly outdoors.
One November morning, the temperature stayed near sixty degrees. Georgia and Rosie completed their usual route to the small park.
Rosie stopped at the bench.
Georgia sat beside her.
They had used that bench during the early weeks, when Georgia’s breathing frightened her and Rosie’s panting forced frequent rests. Now both recovered quickly.
Rosie placed her chin on Georgia’s knee.
After several minutes, they turned home.
The step counter showed 4,800 for Georgia. Rehabilitation added another 2,300. Household movement, a grocery trip, and an evening indoor walk gradually raised the total.
At 7:40 p.m., Georgia stood in the hallway.
The counter read 9,876.
Rosie was asleep on her bed.
I expected my mother to march around the room until the display changed. Instead, she looked at the dog and sat down.
“She’s done,” Georgia said.
“You could walk the hallway yourself.”
“I could.”
She considered it.
Then Rosie woke, stretched, and walked toward the back door for her final bathroom trip. Georgia clipped on the teal leash.
They crossed the yard slowly.
When they returned, the counter read 10,014.
Georgia did not cheer. She removed Rosie’s harness, checked her paws, and wrote the number on the refrigerator chart.
Beside it, she added: “Rosie chose the last steps.”
Ten thousand became an occasional result rather than a daily demand. By the tenth month, Georgia averaged near that number across most days, combining rehabilitation, home movement, and several safe walking periods.
Rosie averaged the veterinary exercise appropriate for her condition. No one claimed she took 10,000 human steps or needed to match Georgia’s tracker.
Then winter introduced another setback.
Rosie began limping after rising from sleep. The limp improved after several minutes but returned following longer walks.
Dr. Grant found progression in the arthritis of her left knee. Weight loss had reduced stress but could not reverse existing joint changes. Rosie required an adjusted pain-management plan, shorter walks, and several weeks of rehabilitation exercises.
Georgia reacted as though they had failed.
“We did everything.”
Dr. Grant answered carefully.
“You improved what could be improved. You did not make her eight years younger.”
That sentence changed our expectations again.
Rosie’s walks became shorter. Georgia continued her remaining steps with me, at cardiac rehabilitation, or inside the house. She no longer abandoned movement simply because Rosie rested.
Each morning, however, she still began with the dog.
Some days they reached only the mailbox.
Georgia counted those as the most important steps of the day.
A canine rehabilitation technician taught Rosie controlled weight shifts, gentle sit-to-stand movements, and slow walking over flat foam bars. Georgia performed her own balance exercises nearby.
They worked in parallel.
By month twelve, Rosie’s limp had decreased, although arthritis remained part of her life. She wore the teal harness on every outing and never walked beyond the distance she chose.
Georgia’s cardiologist repeated functional testing. Her endurance had improved substantially from the first post-surgical evaluation. Blood pressure readings were more stable, and she could complete daily activities with less assistance.
No physician credited a dog alone.
Surgery, medication, rehabilitation, nutrition, family support, monitoring, and Georgia’s own effort all mattered.
Rosie had provided something medicine could not package easily:
a reason to begin before motivation arrived.
Part 6 — The Prescription That Wasn’t Written on a Pad
Dr. Levin asked Georgia about Rosie during nearly every appointment.
At first, he wanted to know whether handling a large dog created fall risk. Later, he asked how often they walked, where they rested, and whether Georgia continued on days when Rosie could not.
My mother brought both refrigerator charts to the clinic.
One tracked her blood pressure, symptoms, rehabilitation, steps, and weight. The other tracked Rosie’s meals, medication, walks, gait, paw condition, and weight.
Dr. Levin studied them.
“You kept better records for the dog,” he said.
“She can’t write her own.”
The idea of recommending rescue-dog walking began there, but it did not become a physician casually handing vulnerable patients an animal.
Owning a dog can create financial, physical, and emotional demands. Some cardiac patients have balance limitations, allergies, housing restrictions, or no ability to manage veterinary care. A large dog pulling on a leash could cause serious injury.
Dr. Levin contacted the hospital’s rehabilitation coordinator and a local rescue liaison. Together, they developed a small voluntary program.
Participants required medical clearance. They did not immediately adopt dogs. Some walked calm shelter dogs inside fenced areas with trained handlers. Others helped with short foster visits or walked a family member’s dog.
The rescue selected animals based on leash behavior, size, health, and tolerance for slow movement.
The instruction was not “get a rescue dog.”
It was “find a safe reason to walk consistently.”
For certain patients, a dog could become that reason.
Georgia attended the first orientation with Rosie. She did not give a speech about miracles. She demonstrated how she checked pavement temperature, carried water, watched for panting, and allowed Rosie to turn home.
“You don’t borrow a dog to make yourself healthy,” she told the group. “You take responsibility for whether the dog is healthy too.”
The first participant was a sixty-eight-year-old man recovering from bypass surgery who began walking an older spaniel inside the rescue courtyard. Another was a retired teacher who fostered a small terrier while completing rehabilitation after a cardiac event.
Over the following months, thirty medically cleared patients participated in some form. Not all adopted. Several decided dog ownership was inappropriate but continued walking through the supervised program.
Dr. Levin jokingly referred to the referrals as his “rescue-dog prescriptions,” though the actual care plans remained ordinary clinical instructions for safe activity.
Georgia enjoyed the phrase.
Rosie did not care.
By month fourteen, my mother’s weight had decreased by approximately eleven kilograms—just over twenty-four pounds—under medical and nutritional supervision. Her exercise tolerance, blood-pressure control, and several cardiac rehabilitation measures had improved.
Rosie had lost approximately six kilograms, a little over thirteen pounds. She weighed just under seventy-one pounds, close to the long-term range Dr. Grant considered appropriate.
The visible change was clear. A waist curved behind her ribs. Her abdomen no longer swayed with every step, and she rose with less effort.
She was not a thin young athlete.
She remained an eight-year-old dog with chronic arthritis requiring management.
Georgia remained an eighty-nine-year-old cardiac patient taking medication and attending follow-up care.
Neither had graduated from having a body that required attention.
Their daily totals varied. Georgia reached or exceeded 10,000 steps on many days, but heat, illness, fatigue, and medical appointments changed the number. Rosie continued shorter veterinary-approved walks rather than accompanying every step.
One January morning, Georgia developed a respiratory infection. Dr. Levin instructed her to pause outdoor walking until symptoms improved.
Rosie waited beside the cane.
Georgia touched the teal leash but did not pick it up.
For five days, I walked the dog while my mother rested. Rosie returned each morning, smelled Georgia’s hands, and lay beside her chair.
My mother followed medical instructions even though the routine had become deeply important.
That choice demonstrated how much she had changed.
Early in recovery, fear had kept her from moving.
Now judgment allowed her to rest.
When Dr. Levin cleared her to resume, the first walk returned to the original route.
Door.
Driveway.
Gate.
Seventy-two steps.
Georgia touched the gatepost while Rosie smelled the grass.
Neither acted disappointed.
They had learned that starting over was not the same as returning to the beginning.
Part 7 — Ten Thousand Was Never the Most Important Number
Georgia turned ninety during Rosie’s second year with her.
The family planned a morning breakfast, but my mother refused to begin until after the walk. At sunrise, she tied her shoes, picked up the cane she now used mostly for uneven ground, and reached for the teal leash.
Rosie was already waiting.
Her chocolate coat showed gray around the muzzle. The white patch beneath her chin had broadened, and the harness fit differently around a body that was thirteen pounds lighter.
They walked to the park bench.
Georgia sat while Rosie smelled beneath it. The route that once required repeated stops now felt familiar, but neither hurried. Rosie’s arthritis had taught us that speed and distance were never reliable measures of a worthwhile walk.
On the way home, several participants from the hospital program passed them with rescue dogs and trained handlers.
Georgia raised one hand.
Rosie watched the dogs but remained beside her.
The program had reached thirty patients, though outcomes differed. Some improved their daily activity. Some adopted dogs. Others discovered that fostering or supervised walking suited them better.
Nobody received a guaranteed medical result.
What they received was structure, accountability, and another living creature whose limits had to be respected.
At Georgia’s fourteen-month assessment, Dr. Levin reviewed her cardiac function, medication response, blood pressure, weight, balance, and endurance. The improvements were meaningful, but he refused to reduce the story to a before-and-after photograph.
“Rosie didn’t perform the surgery,” he said. “She didn’t replace rehabilitation or medication.”
Georgia nodded.
“She got me to the door.”
That was accurate.
Rosie’s veterinary records told the parallel story. Measured food produced most of the calorie change. Walking preserved mobility and muscle. Pain management allowed movement to remain comfortable. Regular examinations caught the paw injury and arthritis flare before they became larger problems.
Georgia had not cured Rosie through love.
Rosie had not cured Georgia through companionship.
They made the prescribed work harder to avoid and easier to repeat.
Their morning routine continued.
Georgia checked the weather. She filled one bottle for herself and one folding bowl for Rosie. She carried a phone and identification. Before each walk, she watched the dog rise and looked for stiffness.
Rosie watched Georgia too.
If my mother moved unusually slowly, the dog waited near the door rather than pulling forward. We could not know whether Rosie understood heart disease. She had learned the pace of one particular person.
One afternoon, I found the original step chart in a kitchen drawer.
The first entry read:
Georgia: 72 steps.
Rosie: 4 minutes, heavy panting, willing to continue after rest.
Fourteen months later, Georgia had recorded 10,186 steps. Rosie had completed two short walks totaling thirty-two comfortable minutes, with no limp afterward.
The numbers showed change.
The handwritten notes showed partnership.
“Stopped under mesquite tree.”
“Rosie refused hot pavement.”
“Mom walked hallway while Rosie rested.”
“Both tired. Went home early.”
“Good morning. No hurry.”
Those details explained why the plan lasted.
They were allowed to have imperfect days.
At sunset on Georgia’s ninetieth birthday, Rosie carried the teal leash from the table and placed it near my mother’s shoes. The dog had never been trained to retrieve it. She had simply learned what object began their shared routine.
Georgia laughed and looked outside.
“We already walked.”
Rosie sat beside the cane.
My mother clipped on the leash anyway. They went only to the gate, where the air had cooled and the streetlights were beginning to glow.
Georgia touched the post.
Rosie smelled the grass.
Then they stood there together, two patients whose doctors had originally asked for movement but could never have prescribed the exact reason either one finally kept going.
Ten thousand steps looked impressive on a chart.
The seventy-two steps they were willing to take again and again were the ones that changed their lives.
Follow the page for more compelling dog-rescue stories about second chances, patient recovery, and the quiet partnerships that help animals and people keep moving forward.