Next part: A Limping Terrier Crawled From a Hospital Laundry Chute in the Basement — Then He Led Police Six Floors Up to a Door Nobody Expected Him to Recognize
Part 2 — The Paw Prints Behind the Loading Dock
The call reached me near the end of my night shift.
Hospital security usually handled loose animals in parking lots or near delivery entrances. A dog emerging from a linen chute created additional questions involving restricted areas, possible injury, and patient safety.
By the time I arrived, the terrier had taken shelter beneath a stainless-steel sorting table.
Only his face and white chest stripe were visible. His ears were flattened. His body shook whenever a cart wheel squeaked across the floor.

The left hind paw was nearly twice the size of the right.
I crouched several feet away and turned my shoulders sideways. Direct approach made him retreat. Food did not interest him.
When the elevator bell sounded, however, he emerged.
His movement was uneven: three short steps, then a brief lift of the injured paw. He reached the closed doors and smelled along the seam.
“He’s been doing that for twenty minutes,” Malik said. “Every time the elevator goes up, he follows it.”
The dog had no reason to understand floor numbers. His reaction could have been connected to scent, sound, or his route through the building.
We needed containment before investigation.
A hospital blanket would have hidden his body and risked pressure on the swollen paw. Instead, I formed a wide loop with a slip lead and placed it on the floor. Malik used a linen cart to create a barrier without cornering him tightly.
The dog stepped through the loop while moving toward the elevator.
I lifted just enough to prevent escape.
He froze, then looked upward at me. No growl. No snap. His mouth closed, and the whites of his eyes showed.
I loosened the lead immediately.
Control did not require choking the fear out of him.
The service elevator stopped on the basement level. A nurse entered, pressed six, and stepped back when she saw the dog.
The terrier pulled forward.
That behavior led to the supervised trip upstairs. Malik obtained authorization from the charge nurse, and the elevator was cleared of other passengers. We placed absorbent pads beneath the dog but did not force him to lie down.
At floor six, his nose moved rapidly.
He turned left before the doors fully opened.
Pip—as we later learned he was called—passed the staff station and traveled approximately seventy feet. He stopped once when his injured foot slipped, then continued to room 614.
The door was closed.
He smelled the narrow gap beneath it and lowered himself across the threshold.
Nurse Claire Bennett checked the room assignment. Eleanor Price, eighty-eight, had been admitted twenty-one days earlier after a neighbor found her unconscious following a cardiac event complicated by a prolonged loss of oxygen.
Her condition had improved medically, but she remained in a disorder of consciousness. She opened her eyes at times without consistently following commands. No physician could predict the timing or extent of recovery.
The dog’s arrival did not change that reality.
At first, nobody knew whether Pip had identified Eleanor or merely followed a familiar scent into a random hallway. Then Claire found the note in Eleanor’s admission record.
The notation had been made by a social worker after Marlene Brooks agreed to check the house.
“Small terrier at residence.”
We called Marlene.
She identified him from a photograph of his white chest stripe and blue collar. She also supplied his name, veterinary clinic, and vaccination history.
Pip had lived with Eleanor for seven years.
He was approximately nine years old and weighed nineteen pounds. He slept beside her recliner and followed her from room to room. When paramedics removed Eleanor, they could not transport him. Marlene took responsibility for feeding him until a relative arrived from out of state.
The relative’s travel was delayed.
Pip remained in the familiar house with daily visits but no person staying overnight.
Three days before the hospital call, a storm loosened the backyard latch. Pip disappeared.
Marlene had searched a two-mile area, unaware that he had traveled toward the medical center.
The direct road distance was approximately six kilometers. We could not know the exact route or whether someone briefly picked him up along the way. His abraded paw pads, dehydration, and exhaustion were consistent with substantial travel.
Security began reviewing footage.
At 11:47 the previous night, Pip appeared at the loading dock behind a covered food-delivery cart. He entered when an employee held the door open for the cart operator, never noticing the small dog on the far side.
Pip moved along the wall, avoiding people.
Twenty minutes later, another camera recorded him stepping into a service elevator behind a laundry employee. He exited at floor six.
The dog had not climbed six flights.
He had followed hospital movement the way a frightened dog follows openings: one door, one cart, one elevator at a time.
At 12:31, staff spotted him near the ICU and attempted to contain him. Pip ran into the linen utility room. Maintenance had opened the chute access because workers were investigating a blockage below.
He slipped through the service barrier before anyone could close it.
The jammed linen prevented a free fall, but the chute remained dangerous. Pip had crawled and slid through compressed bags until reaching the basement pile.
His search had nearly killed him.
We could not let him repeat it.
As we moved Pip away from Eleanor’s door, he planted his front feet and looked backward. His body was too exhausted for resistance to last.
The veterinary clinic sent a transport team.
Pip left the sixth floor on a stretcher pad, his swollen paw supported and his face turned toward room 614.
He had reached her door, but recognition alone could not yet earn him entry.
Part 3 — Two Medical Teams and One Closed Door
Pip’s veterinary examination began with the injuries we could see.
His left hind paw contained a small puncture between two toes, likely caused by road debris. Swelling spread across the soft tissue, but radiographs found no fracture. All four pads were worn and superficially abraded.
He was mildly dehydrated and had lost weight during the three days away from home.
More concerning was a rounded swelling along the outside of the left paw, covered by intact skin and short hair. Marlene said the area had been smaller before Pip disappeared.
Dr. Aisha Patel cleaned the puncture, examined the swelling with ultrasound, and collected a needle sample. The findings were consistent with acute inflammation around an infected foreign-body tract rather than a tumor.
A small plant fragment was removed.
Pip received fluids, antibiotics, pain medication, and a padded bandage. He was required to rest. Walking the ICU hallway again was not medically appropriate that day.
The clinic also confirmed his identity through his microchip and vaccination records. Parasite screening was negative. His coat was cleaned with a waterless veterinary product because a full bath would have been stressful and could wet the bandage.
These steps satisfied only the animal-health side.
An ICU visit required approval from Eleanor’s medical team, hospital administration, and infection prevention. Pip could not enter during sterile procedures, medication preparation, or periods of medical instability.
Eleanor could not personally consent.
Her niece, Patricia Lane, served as medical decision-maker. She was traveling from Colorado and joined the discussion by video call.
Patricia recognized Pip immediately.
“He sleeps on her feet,” she said. “She leaves the television on for him when she buys groceries.”
She authorized a controlled visit if the medical team believed it safe.
The attending physician, Dr. Rebecca Shaw, warned everyone against framing the visit as a treatment expected to wake Eleanor. Familiar voices, music, touch, and scent may be used as supportive stimulation in some neurological care plans, but responses vary widely.
Pip’s presence could offer comfort.
It could also have no measurable neurological effect at all.
The family understood.
The first visit was scheduled for the following afternoon if both patients remained stable.
Pip spent the night at the veterinary clinic.
He did not eat until a technician placed Eleanor’s blue cardigan near his kennel. Marlene had brought it from the house after confirming hospital permission.
Pip smelled the sleeve, circled twice, and lay on it.
Later, he ate half a meal.
That was his first small sign of settling since leaving the basement.
Meanwhile, Eleanor experienced a fever overnight. The ICU team postponed the visit while evaluating her for infection.
Nobody argued.
Pip stayed at the clinic for another day. His paw swelling decreased, but he became restless whenever people passed his kennel. He repeatedly carried the cardigan toward the door.
Marlene offered to foster him until Eleanor’s condition became clearer. Pip knew her, and her home was one block from his own. The rescue partner assisting the hospital provided a crate, medication chart, and transport.
At Marlene’s house, Pip moved from room to room before settling near the front door. He refused the dog bed and slept on Eleanor’s cardigan.
The following morning, he tried to walk toward Eleanor’s house.
Marlene used a short leash and returned him indoors. The bandaged paw required rest, and the backyard gate had been secured.
Pip did not understand why every route remained closed.
He had already crossed the city, entered the hospital, reached the correct floor, and found Eleanor’s door. From his perspective, people kept carrying him away just before he reached her.
His stress began affecting recovery. He licked at the bandage and loosened the upper edge. Dr. Patel replaced it and fitted a soft protective collar.
The collar frightened him.
He backed into furniture and refused food.
Instead of forcing continued use, the clinic changed to a lighter inflatable collar under direct supervision and added a breathable paw covering for brief bathroom trips.
The visit remained postponed for forty-eight hours until Eleanor’s fever resolved.
When approval finally came, the conditions were strict.
Pip would enter through a private service route. Only one handler would accompany him. The bandage would be covered by a clean disposable boot. He would remain on a washable mat beside the bed for no longer than fifteen minutes.
Marlene brought him to the hospital in a secured crate.
At the sixth-floor elevator, Pip began whining.
When the doors opened, he pressed toward the front of the crate, nose working rapidly.
The team carried him to room 614.
This time, the door opened before anyone asked him to leave.
Part 4 — The Fifteen-Minute Visit
Eleanor’s ICU room was quieter than the hallway.
Ventilator support was no longer required, but monitors tracked her heart rhythm, oxygen level, and blood pressure. A feeding tube remained in place. Her eyes were closed when Pip entered.
Dr. Shaw, Claire, an infection-control nurse, Marlene, and Patricia were present. Patricia had arrived that morning after traveling through the night.
The room was crowded by ordinary ICU standards, so everyone except Marlene stepped back.
Pip’s crate was placed on the floor beside the bed.
Marlene opened the door.
He smelled the air but did not exit immediately. The clean disposable boot changed how his injured paw contacted the floor, and the medical equipment produced unfamiliar beeps and airflow.
Then Eleanor shifted her head slightly.
Pip came out.
He moved toward the bed until the leash reached its safe limit. The mattress stood too high for him to see her clearly, so staff lowered it within clinical limits.
Marlene lifted Pip using support beneath his chest and abdomen, avoiding the injured paw. She placed him on a washable blanket beside Eleanor’s legs, not near lines or equipment.
Pip stood for several seconds.
Then he smelled Eleanor’s hand.
His whole body softened.
He lowered himself against her calf, resting his chin near her wrist. The blue cardigan remained beneath him.
Nobody spoke for almost a minute.
Pip did not bark, lick her face, or perform any dramatic action. His breathing slowed. The trembling in his shoulders stopped.
Eleanor’s monitor readings remained stable.
Patricia said his name softly.
Pip raised one ear but did not leave Eleanor’s side.
Claire guided Eleanor’s hand so it rested lightly against the blanket near Pip’s back. There was no visible purposeful response.
The visit lasted thirteen minutes.
When Marlene lifted Pip, he resisted by pressing his chest downward. She waited until he relaxed, then returned him to the crate.
He whined once as they left.
The door closed again.
The staff documented the session as a family-supported animal visitation, not a medical intervention. There was no immediate change in Eleanor’s neurological examination.
Pip returned to Marlene’s home and slept for nearly six hours.
The following day, the visit was repeated. His paw swelling continued improving, and Dr. Patel approved brief weight-bearing. This time, Pip walked from the elevator to the room under control.
He recognized the turn.
At the doorway, his tail moved once.
Inside, he settled more quickly. Marlene placed him on the blanket beside Eleanor’s legs. Patricia spoke about home, the backyard, and Pip sleeping beneath the kitchen table.
During the visit, Eleanor opened her eyes.
She had opened them intermittently before, so the action alone did not indicate recovery. Dr. Shaw asked her to look toward Patricia. Eleanor’s gaze moved but did not hold consistently.
Then Pip shifted against her leg.
Eleanor’s fingers flexed.
The response was small and could not be interpreted from one observation. The team repeated commands later without the dog present and continued neurological assessments.
That evening, Eleanor showed brief visual tracking toward Patricia’s voice.
The next morning—two days after Pip’s first bedside visit—she opened her eyes during nursing care and appeared to follow Claire across the room.
Patricia leaned near her.
“Aunt Eleanor, do you know who’s here?”
Eleanor’s lips moved, but no clear sound emerged.
Later that afternoon, Pip returned for a third controlled visit.
He lay against her legs.
Eleanor opened her eyes and looked downward.
Her mouth moved again.
This time, Patricia heard one word.
“Pip.”
The room remained quiet.
Claire asked Eleanor to repeat it. She could not.
Dr. Shaw recorded the response but cautioned that recovery after prolonged unconsciousness often fluctuates. One meaningful word did not guarantee a full return of cognition, independence, or speech.
Pip had not medically awakened her.
His presence coincided with a period when Eleanor’s injured brain was beginning to produce purposeful responses. His familiar scent, weight, and movement may have provided recognizable stimulation, but no one could isolate cause from timing.
For Patricia, the distinction mattered medically but not personally.
Her aunt had spoken the dog’s name.
Pip rested his chin against Eleanor’s leg, apparently unaware that anything in the room had changed.
Part 5 — The Patient Who Could Not Go Home Yet
Eleanor’s recovery did not move in a straight line after she said Pip’s name.
The next morning, she did not speak. She opened her eyes only briefly and failed to follow several commands she had completed the previous day.
Patricia feared the improvement had disappeared.
Dr. Shaw explained that fluctuating responsiveness was common. Fatigue, medication, infection, sleep disruption, and neurological injury could all affect performance.
The team continued therapy.
Pip’s visits remained short and were canceled whenever Eleanor needed rest or procedures. He never entered the room automatically. Each visit required approval.
At Marlene’s house, his own recovery continued.
The left hind paw puncture closed, and swelling decreased. The rounded area remained visible for another week but gradually returned toward normal size. He completed antibiotics and transitioned from a full bandage to a protective boot used only outdoors.
The six-kilometer journey had also worn all four pads. Short bathroom walks were permitted, but no long routes.
This restriction became a practical obstacle.
Pip repeatedly pulled toward the direction of the hospital.
Marlene began transporting him by car for approved visits so he would not attempt the route himself. The crate remained secured, and the blue cardigan traveled with him.
During the second week of visits, Pip developed redness around the healing paw from moisture beneath the boot. Dr. Patel instructed Marlene to remove it indoors, dry the foot carefully, and limit use.
The setback delayed one hospital trip.
Pip spent that afternoon lying beside the front door.
By then, Eleanor could answer simple yes-or-no questions inconsistently. Speech therapy documented several recognizable words. Physical therapists helped her sit upright with support.
When Patricia showed her a photograph of Pip, Eleanor’s gaze remained on the image.
“Dog,” she whispered.
“Yes,” Patricia said. “Pip.”
Eleanor closed her eyes.
Recovery required energy she did not yet possess.
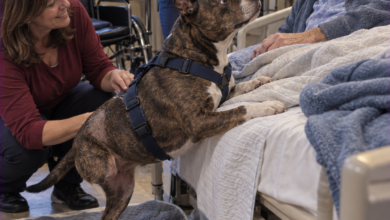
On Pip’s next visit, staff placed him on a chair beside the bed rather than on the mattress. A secure harness attached to a short lead prevented him from approaching equipment.
Eleanor turned her head toward the sound of his tags.
Pip stood with his front paws at the chair edge.
She moved her hand.
The distance between them was less than a foot, but neither could cross it without assistance. Claire supported Eleanor’s forearm while Marlene steadied Pip.
Eleanor’s fingertips touched the white stripe on his chest.
Pip became still.
The contact lasted four seconds.
Then Eleanor’s arm tired and lowered.
It was not the reunion imagined in dramatic stories. She did not sit up. Pip did not leap into her arms. Nobody declared the crisis over.
Four seconds were enough.
Over the following two weeks, Eleanor transitioned from intensive care to a step-down neurological unit. Pet access there required a new review because rooms were shared and rehabilitation schedules differed.
The hospital arranged visits in a private therapy room after other patients had left. Environmental services cleaned the space afterward, and Pip entered through a designated route.
His presence became part of Eleanor’s familiar-orientation sessions alongside photographs, music, and recorded family voices.
Again, the team did not call Pip a treatment.
He was a member of her household whose visits could be accommodated safely.
Eleanor began forming short sentences. She remembered Pip consistently before she remembered the date. She sometimes believed she was still at home and asked who had fed him.
Marlene answered each time.
“I did. He’s safe.”
Pip also showed changes. He stopped pulling toward every hospital doorway. When visits ended, he entered his crate with less resistance because he had learned that leaving did not always mean losing access forever.
That lesson generalized slowly.
At Marlene’s house, he began sleeping on a dog bed rather than Eleanor’s cardigan. He still carried the sleeve into the bed but no longer lay directly across the front door all night.
Three weeks after the first visit, Eleanor entered inpatient rehabilitation.
Her projected stay was uncertain. She needed assistance standing, transferring, eating, and completing basic tasks. Returning to her old house would require support and accessibility changes.
Patricia considered moving Eleanor near her home in Colorado.
Eleanor resisted.
When asked why, she answered with one clear sentence:
“Pip knows our yard.”
The statement did not decide discharge planning. Safety, caregiving, and medical needs came first.
But it reminded everyone that home, for Eleanor, was not simply an address.
It was the place where a nineteen-pound dog expected her chair to be occupied.
Part 6 — Building a Safer Way for Animals to Visit
Pip’s entry through the laundry chute led to an internal hospital review.
The purpose was not to celebrate how he entered.
His route exposed security and safety failures. A dog had followed carts through loading areas, entered a service elevator, reached an ICU corridor, and accessed an open linen chute during maintenance.
Any one of those events could have ended differently.
The hospital installed lower visual barriers near the loading entrance, revised cart-entry checks, and required chute service doors to remain physically guarded whenever open. The linen blockage that cushioned Pip’s descent was treated as a fortunate accident, not a rescue method.
At the same time, staff reviewed the controlled visits that followed.
Patients had occasionally received therapy-animal visits, but those dogs belonged to certified programs and did not know the patients personally. Personal-pet visits required improvised approvals.
Eleanor’s case led the hospital to create a formal pilot policy.
It did not grant unrestricted ICU access.
A patient or authorized decision-maker had to request the visit. The medical team assessed whether the patient was stable. Infection-prevention staff reviewed the room and timing. The animal required veterinary records, hygiene screening, current vaccinations, parasite control, calm handling, and a designated adult responsible for transport.
Some patients and pets would not qualify.
The program’s purpose was safe family connection, not a promise of recovery.
Pip became the first dog processed under the completed protocol, though his initial visits had occurred before the policy was finalized.
Marlene attended handler orientation. Pip practiced entering the hospital through the public side entrance, crossing nonslip mats, waiting at elevators, and ignoring food on the floor.
He was not converted into a therapy dog.
He learned only the behaviors needed for visiting Eleanor safely.
His swollen paw healed, but a faint thickened area remained between the toes for several months. Dr. Patel continued checking it because retained plant material could cause recurrence.
The worn pads recovered fully.
Pip’s larger setback came during rehabilitation month.
Eleanor had been improving steadily when she developed another infection. Visits paused while she received treatment, and her strength declined. She slept more and participated less in therapy.
Pip returned to Marlene’s front door routine.
He ate, but only after the blue cardigan was placed nearby. On walks, he pulled toward the end of the block where the road led generally toward the hospital.
Marlene did not let him walk the six-kilometer route.
She drove him only when the hospital approved.
After nine days, Eleanor stabilized. Her first renewed visit occurred in the therapy courtyard, where Pip could remain on the ground and she could sit in a supported wheelchair.
When he saw her, he approached slowly.
The wheelchair was new to him. He smelled the footrests, circled once, and sat beside the right wheel.
Eleanor lowered her hand.
Pip placed his chin beneath it.
For twelve minutes, neither moved more than necessary.
The setback had not erased recognition.
Therapists later incorporated simple dog-care tasks into Eleanor’s functional goals when appropriate: filling a lightweight water dish, clipping a leash to a stationary practice loop, and giving verbal cues.
Pip did not attend every session.
The goal was to help Eleanor regain skills, not make the dog responsible for her performance.
By the end of the month, Eleanor could stand with a walker and assistance. She could eat most meals safely and hold short conversations, though memory gaps remained.
Discharge planning settled on her original home with daytime caregiving, home-health visits, safety modifications, and Patricia remaining locally during the transition. Marlene agreed to continue helping with Pip.
The date was scheduled almost seven weeks after Pip emerged from the basement linen.
The evening before discharge, he visited Eleanor’s hospital room one final time.
She looked at his healed paw and asked, “How did you find me?”
No one in the room could answer completely.
Scent may have played a role. Familiar vehicle routes, hospital odors carried on paramedics, random movement, and opportunity may all have contributed.
Security footage showed where Pip went.
It could not show what information his nose followed or why he continued after every wrong turn.
Eleanor touched the white stripe on his chest.
“You took the laundry,” she said.
Pip closed his eyes beneath her hand.
Part 7 — The Chair Was Occupied Again
Eleanor returned home on a cool Friday morning.
A ramp had been installed at the front entrance. Grab bars lined the bathroom, medication filled labeled organizers, and a home-health nurse was scheduled for the afternoon.
Pip arrived first with Marlene.
He inspected every room, smelled the new equipment, and stopped beside Eleanor’s recliner. The blue cardigan lay across one arm exactly where it had before the emergency.
When the medical transport vehicle entered the driveway, Pip ran toward the window.
Marlene clipped his leash before opening the door.
Eleanor came inside using a walker with Patricia beside her. She moved slowly and tired after only a few steps.
Pip did not jump.
He approached the walker, smelled the wheels, and stood close enough for Eleanor to touch his head.
Then he walked beside her toward the recliner.
The journey from door to chair took nearly three minutes.
Pip waited.
When Eleanor sat down, he circled beside her feet and lowered himself across the rug. His healed left hind paw rested beneath him.
For the first time in almost two months, the chair and the dog were occupied together.
Eleanor’s recovery continued at home. She never regained every ability she had before the medical emergency. She required help with meals, medication, transportation, and some daily tasks.
Pip’s care also changed.
The backyard latch received a secondary lock. He wore an identification tag and GPS tracker in addition to his microchip. Marlene kept an emergency plan authorizing temporary pet care if Eleanor returned to the hospital.
Nobody wanted another six-kilometer search.
The hospital’s personal-pet visitation pilot began with six approved cases during its first months. Some involved ICU patients; others involved long rehabilitation stays or end-of-life care.
Not every request was possible. Animals displaying distress, illness, poor control, or uncertain vaccination status could not enter. Some visits occurred outdoors or by glass.
The policy existed because Pip’s controlled visits showed that personal animals could sometimes be included without ignoring clinical safety.
It did not claim animals awakened patients.
Eleanor’s medical team remained clear: her recovery resulted from stabilization, treatment, rehabilitation, time, and the complex course of neurological healing. Pip’s arrival occurred near the beginning of purposeful responses, and his familiar presence may have offered meaningful sensory and emotional context.
That was enough.
Months later, I visited Eleanor while following up on the original incident report.
She remembered my uniform but not my name. She remembered Pip’s route more clearly because Patricia had told the story many times.
“He came through the laundry,” Eleanor said.
“Unfortunately, yes.”
She looked down at him.
Pip was asleep beside the recliner, his body pressed against one of her slippers.
The swelling on his left paw had resolved, though a small pale scar remained between the toes. His blue collar had been replaced, but the white chest stripe and careful way he rose after resting were unchanged.
Eleanor reached for him.
Pip stood and placed his front paws lightly against the footrest, allowing her to touch his ears.
He no longer needed to search hallways, follow carts, wait beside elevators, or force himself through a dark chute.
She was where he expected her to be.
Near the front door hung a framed photograph taken during one of the approved courtyard visits. Eleanor sat in her wheelchair while Pip rested beside the right wheel.
The image did not show the basement, ICU monitors, or linen chute.
It showed a woman and her dog occupying the same patch of daylight.
Before I left, Eleanor asked how far Pip had walked.
“About six kilometers, as best we can estimate.”
She shook her head.
“He hates long walks.”
Pip looked up at the sound of her voice.
The absurdity of it made her laugh—briefly, quietly, but clearly.
He had crossed a distance he normally avoided, entered a building he had never known, reached the sixth floor, survived the linen chute, and returned to her door after being carried away.
We could explain portions of the route with cameras and floor plans.
We could never fully explain the persistence.
Pip settled beside her slipper again.
He had spent three days trying to reach the woman who could not call him; now one soft word from her chair was enough to bring him home.
Follow the page for more compelling dog-rescue stories about impossible journeys, careful second chances, and the quiet bonds that refuse to disappear when families are separated.